
Myofascial Trigger Point Dry Needling for Subscapularis and Infraspinatus Spasm in Frozen Shoulder
In short
Myofascial trigger points in the subscapularis and infraspinatus lock the frozen shoulder. Discover how dry needling releases muscular contractures safely.
In this guide (4 sections)
In adhesive capsulitis, the profound loss of rotational mobility is driven by a dual pathology: structural contracture of the glenohumeral capsule and intense myofascial trigger point formation within the surrounding rotator cuff musculature. The subscapularis and infraspinatus muscles, subjected to chronic protective spasm, develop hypersensitive taut bands and active trigger points that continuously refer deep, aching pain into the shoulder and arm. Deep palpation of the subscapularis inside the axillary fossa is often exquisitely painful and mechanically blocks external rotation. Myofascial trigger point dry needling, performed by certified physiotherapists, provides a targeted, minimally invasive modality to mechanically disrupt these taut bands and reset muscular resting tone.
Indian Household Realities: Relieving Deep Aches and Overcoming Apprehension
In Indian clinical practice, patients suffering from chronic frozen shoulder often report an agonizing, heavy toothache-like sensation deep in the armpit and back of the shoulder blade. This deep muscular pain makes it agonizing to rest the arm while sitting, read a book, or relax with family. Many patients try local rubs, herbal poultices, or intense unguided massages, but traditional surface pressure cannot reach the deep subscapularis belly hidden within the axilla. While some individuals initially feel apprehensive about needles, learning that fine, solid acupuncture-type needles produce a brief, deep twitch response followed by immediate muscular release provides enormous relief and restores motivation.
Neurophysiology of the Local Twitch Response and Chemical Washout
Active myofascial trigger points feature sustained sarcomere contractures driven by excessive, uncoordinated acetylcholine release at the motor endplate. This localized contracture creates capillary compression and severe focal hypoxia, resulting in an acidic microenvironment rich in inflammatory mediators, including substance P, calcitonin gene-related peptide (CGRP), bradykinin, and tumor necrosis factor. When a fine filiform needle penetrates the taut band, it provokes a rapid involuntary local twitch response (LTR). This mechanical disruption instantly depolarizes the contracted muscle fibers, terminates spontaneous electrical endplate noise, and stimulates localized hyperemia that flushes out acidic neurochemical mediators, restoring normal cellular pH and muscle resting length.
Clinical Needling Protocol: Anatomical Precautions, Piston Technique, and Post-Needle Mobilization
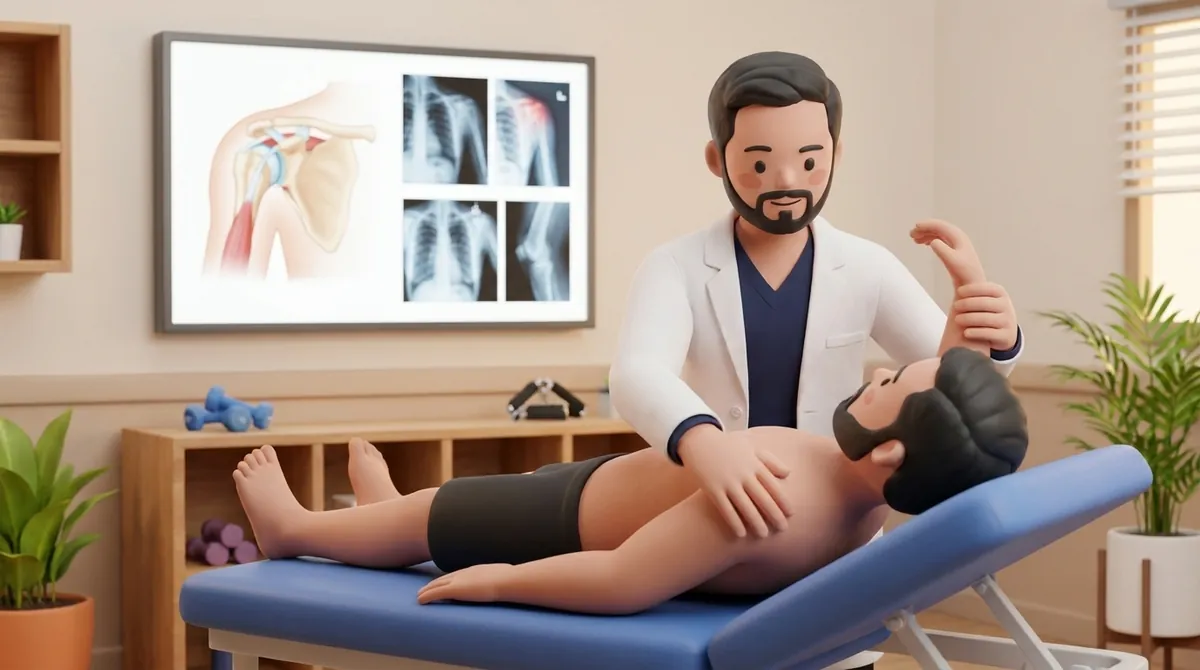
Dry needling in the shoulder girdle demands rigorous anatomical precision. For the subscapularis, the patient lies supine with the arm abducted to 60 degrees; the clinician palpates the lateral border of the scapula in the axillary space, gently compressing the muscle belly against the anterior scapular surface while angling the needle strictly away from the thoracic wall to eliminate any risk of pneumothorax. For the infraspinatus, needling is performed in prone or side-lying position directly into the infraspinatus fossa, using the flat scapular blade as a solid bony backstop. Following trigger point deactivation, the physiotherapist immediately performs gentle active-assisted range of motion drills to integrate the newly gained muscular compliance.
Post-Needling Active-Assisted Subscapularis Elongation
Objective: Elongate the newly deactivated subscapularis muscle fibers following dry needling using gentle wand guidance
- 1Lie comfortably on your back on a firm bed, placing a rolled hand towel under the elbow of your treated arm.
- 2Keep your elbow bent at 90 degrees and tucked snugly against your ribcage.
- 3Hold a light wooden wand with both hands, placing hands slightly wider than your shoulders.
- 4Use your unaffected arm to push the wand gently across your body, guiding the treated forearm outward into external rotation.
- 5Pause at the first point of comfortable stretch, hold for 15 seconds while breathing slowly, then slowly return.
| Target Muscle Group | Needle Orientation & Anatomical Landmark | Safety Precautions & Avoided Structures |
|---|---|---|
| Subscapularis (Anterior Scapula) | Arm abducted to 60°; lateral axillary approach into subscapular fossa against ventral scapula. | Direct needle strictly parallel to scapular blade; never aim medially toward the thoracic wall or pleura. |
| Infraspinatus (Posterior Scapula) | Prone or side-lying; needle inserted perpendicularly onto the broad infraspinatus bony fossa. | Bone backstop ensures safety; avoid penetrating the suprascapular notch or lateral axillary margin. |
| Upper Trapezius / Levator Scapulae | Pincer grasp lifting muscle belly upward off the apex of the lung; needle angled anteroposteriorly. | Strict pincer hold mandatory; never needle straight down into the supraclavicular fossa. |
| Teres Minor & Posterior Deltoid | Side-lying; needle directed onto the mid-lateral border of the scapula. | Avoid deep inferior insertion to protect the quadrilateral space and axillary nerve. |
Dry needling must strictly adhere to universal aseptic precautions using sterile, single-use filiform needles. Absolute contraindications include local skin infections, lymphedema, active anticoagulant therapy, or compromised immune status. If a patient experiences sudden shortness of breath, chest pain, or coughing following needling around the shoulder girdle, emergency evaluation for pneumothorax is mandatory. Acute joint effusion requires medical evaluation to exclude septic arthritis.
Frequently Asked Questions
Is dry needling the same thing as traditional Chinese acupuncture?
No, dry needling is not acupuncture. While both techniques use similar fine, sterile needles, acupuncture is based on traditional energy meridians, whereas dry needling is a western, evidence-based orthopedic procedure. Physiotherapists use dry needling to target specific knotted muscle fibers (trigger points) in the subscapularis and infraspinatus to physically release muscle spasms and relieve deep shoulder ache.
Do I need a doctor referral to see a frozen shoulder physiotherapist on BookPhysio.in?
BookPhysio.in does not require a physician prescription. Under the National Commission for Allied and Healthcare Professions (NCAHP) Act 2021, patients across India enjoy direct access to autonomous registered physiotherapists. Through BookPhysio.in, you connect directly with verified clinicians and pay per session with transparent fees, completely free from advance package commitments, commission markups, or platform subscription charges.
Related condition guides

Related recovery guides & articles
BookPhysio.in Editorial Team
The BookPhysio.in editorial team writes and maintains this content, checking it against reliable clinical sources. Content follows our medical review policy: general information only, and no page claims a clinical review until a named registered physiotherapist has signed it off.
Read our medical review policy