
Scoliosis Screening: The Scoliometer, Angle of Trunk Rotation (ATR), and Adam's Forward Bend Test
In short
A scoliometer reading >= 5 to 7 degrees during Adam's forward bend test identifies significant axial trunk rotation, serving as the universal trigger for full-spine X-rays.
In this guide (4 sections)
Principles of Surface Topography and Axial Vertebral Rotation
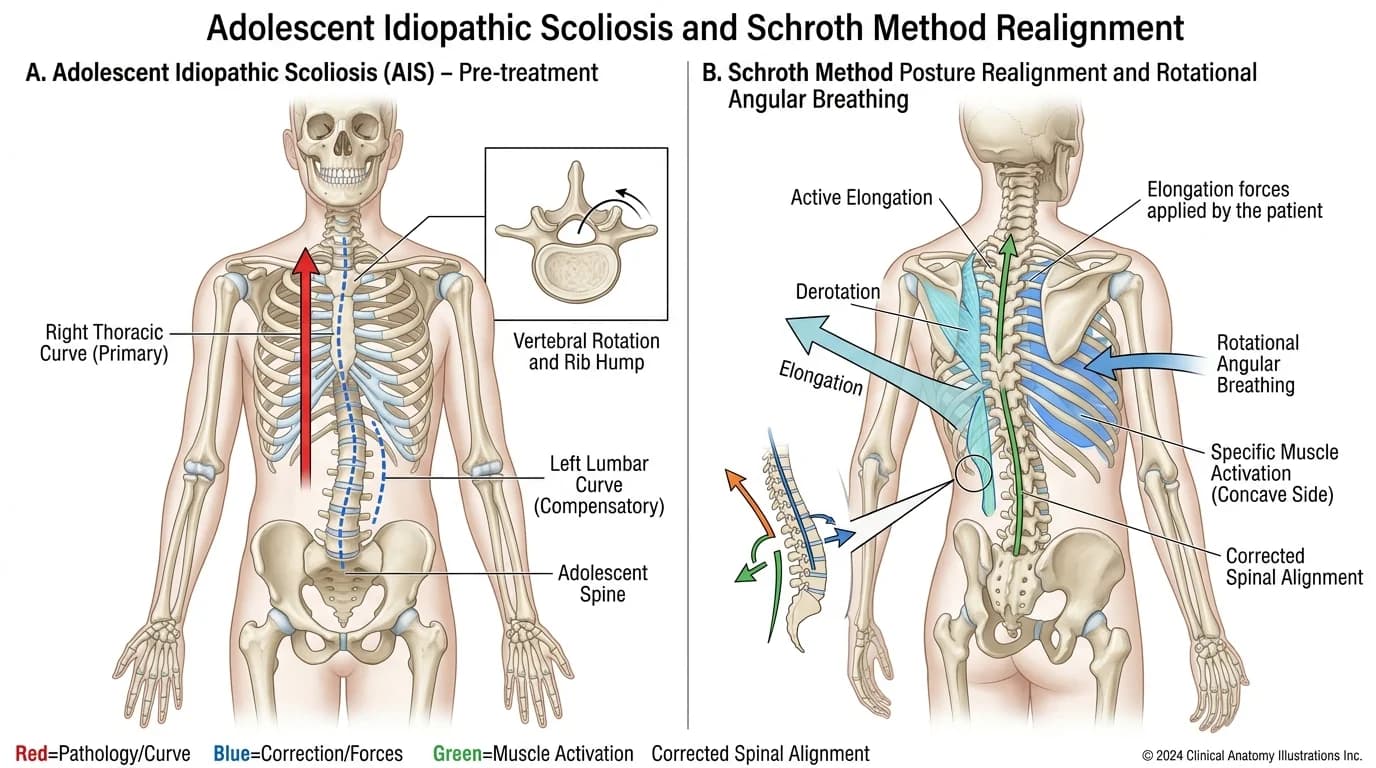
Scoliosis is inherently a three-dimensional deformity where lateral curvature in the coronal plane is coupled to rotational torsion in the transverse plane. As vertebrae rotate toward the convexity of the curve, they carry the attached posterior ribs or lumbar transverse processes with them. In the thoracic spine, this rotation projects the posterior rib cage outward, creating a prominent asymmetric dorsal 'rib hump'.
The Adam's Forward Bend Test is the universal clinical screening tool designed to accentuate this rotational asymmetry by eliminating the confounding effect of limb length discrepancies. Measuring the inclination of this rib hump using a specialized inclinometer (the Bunnell Scoliometer) provides an objective, reproducible proxy of internal 3D spinal torsion.
Scoliometer Angle of Trunk Rotation (ATR) Diagnostic Matrix
| Scoliometer ATR Reading | Estimated Coronal Cobb Angle | Clinical Classification | Mandatory Action / Referral | |
|---|---|---|---|---|
| ATR 0 to 4 degrees | Cobb angle < 10 degrees (physiological asymmetry) | Within normal postural variation limits | No action needed; repeat annual screening if growing | |
| ATR 5 to 6 degrees | Cobb angle ~ 10 to 19 degrees (mild scoliosis) | Borderline structural curve in skeletal immature | Initiate physiotherapeutic scoliosis exercises (PSSE); 6-month check | |
| ATR 7 degrees (Standard Cutoff) | Corresponds to Cobb angle >= 20 to 25 degrees | Definitive clinical screening threshold (SOSORT/SRS) | MANDATORY standing full-spine PA radiograph referral | |
| ATR >= 10 to 12 degrees | Corresponds to Cobb angle >= 30 to 40 degrees | Moderate-to-severe rotational deformity | Urgent orthopedic review for rigid bracing and Schroth therapy | |
| Lumbar ATR vs Thoracic ATR | Lumbar transverse processes produce smaller hump than ribs | ATR of 5 deg in lumbar spine indicates higher Cobb | Lower threshold (5 deg) applies to lumbar prominences |
Standardized Clinical Testing Protocol and Patient Coaching
- The Precise Adam's Forward Bend Positioning: Have the adolescent stand with feet together, knees straight, palms pressed flat together, and arms hanging freely; instruct them to bend slowly forward until the back is horizontal; look from behind at eye level to detect asymmetric paraspinal humps.
- Bunnell Scoliometer Placement and Measurement: Rest the notched center of the scoliometer gently over the spinous processes perpendicular to the long axis of the spine; sweep the device from the upper thoracic spine down to the sacrum; record the peak angle of rotation at both the thoracic and lumbar prominences.
- Eliminating Pelvic Obliquity and Leg Length Discrepancy: If a leg length difference is suspected, place wooden leveling blocks under the shorter foot before testing; leveling the iliac crests prevents a non-structural pelvic tilt from producing a false-positive lumbar ATR reading.
Frequently Asked Questions
What is an Adam's forward bend test for scoliosis?
The Adam's test is a simple screening exam where a teenager puts their hands together and bends forward like diving into a pool. When bending forward, any twist in the spine makes one side of the ribs or lower back stick up higher than the other.
What is a scoliometer and what does it measure?
A scoliometer looks like a curved ruler with a rolling ball inside, similar to a carpenter's level. The therapist places it across the child's back while they bend forward to measure the exact degree of twist (Angle of Trunk Rotation, or ATR).
At what scoliometer number should a child get a spine X-ray?
A scoliometer reading of 7 degrees or higher is the universal medical trigger for an X-ray. A 7-degree reading usually means the underlying spine curve has reached 20 to 25 degrees, which may require a corrective brace.
Related condition guides


Related recovery guides & articles
BookPhysio.in Editorial Team
The BookPhysio.in editorial team writes and maintains this content, checking it against reliable clinical sources. Content follows our medical review policy: general information only, and no page claims a clinical review until a named registered physiotherapist has signed it off.
Read our medical review policy